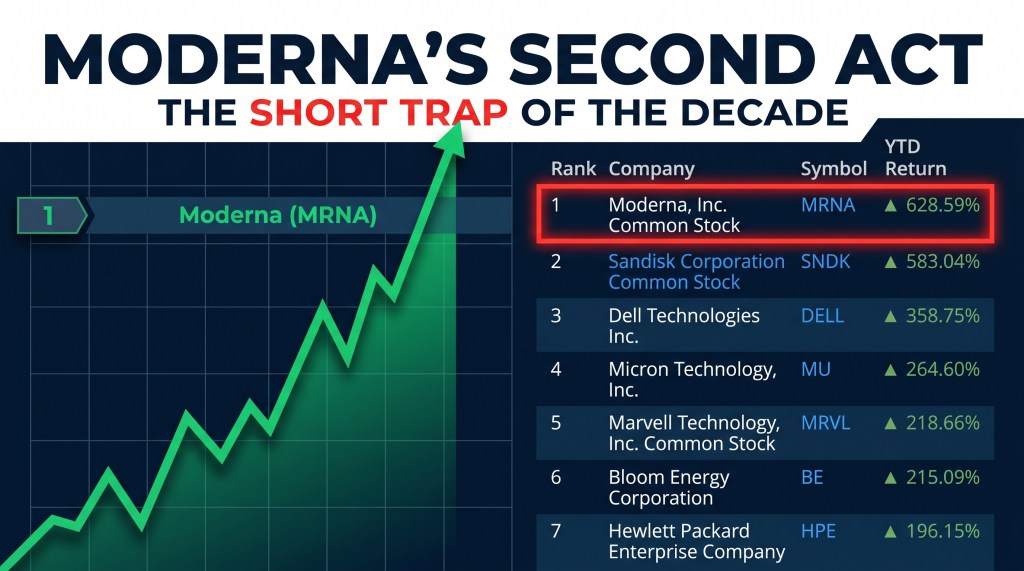
Every few years, the financial commentariat suffers from a collective failure of imagination. When a beaten-down stock catches fire, the reflexive reaction from spreadsheet purists is depressingly predictable: dismiss the rally, call the valuation absurd, and hunt for an entry to short.
Right now, that exact mistake is happening in real time with Moderna (MRNA).
Following the Phase 3 topline readout for its personalized cancer vaccine program (reported August 19, 2026; full data presentation at ESMO on October 24), the bears have retreated to a comfortable, lazy narrative:
“It’s just melanoma. It’s an easy target. Other companies have done this before. The valuation has completely detached from reality.”
Every single part of that thesis is demonstrably false.
Trying to undersell Moderna’s Phase 3 data reveals a fundamental misunderstanding of oncology history. Conflating Moderna with speculative, cash-burning micro-cap biotechs is an egregious category error. And attempting to short a paradigm-shifting biotech platform using a static, single-year Discounted Cash Flow (DCF) model is a classic lesson in how accounts blow up.
Here is what the market is actually looking at—and why this run has far more structural power than the skeptics realize.
1. The Historical Myth: “Other Biotechs Have Done This Before”
Let’s dismantle the biggest myth circulating on financial podcasts and social media: the idea that therapeutic cancer vaccines routinely clear Phase 3 trials in melanoma, or that melanoma represents a “low bar.”
In the entire history of cancer immunology, no personalized neoantigen vaccine had ever cleared a randomized Phase 3 trial until Moderna and Merck’s INTerpath-001. Full stop.
For over thirty years, Big Pharma poured tens of billions of dollars into therapeutic cancer vaccines, specifically targeting melanoma because of its high tumor mutational burden (TMB). The result was not a track record of easy wins—it was an absolute graveyard:
- Canvaxin (CancerVax): A whole-cell vaccine halted mid-Phase 3 in the mid-2000s when vaccinated patients showed zero survival benefit over placebo.
- MAGE-A3 (GlaxoSmithKline): The massive DERMA trial enrolled over 1,300 melanoma patients targeting shared antigens. It collapsed completely in 2014, failing to improve disease-free survival.
- Allovectin-7 (Vical): A plasmid-based immunotherapy was obliterated in Phase 3 in 2013 against basic dacarbazine chemotherapy.
- gp100 Peptide Vaccines: Routinely failed monotherapy Phase 3 trials for decades, eventually relegated to being the baseline control arm that Bristol Myers Squibb outperformed to approve Yervoy.
Whenever bears claim “cancer vaccines have worked before,” they invariably point to two historical outliers that share zero mechanistic overlap with Moderna’s platform:
- Sipuleucel-T (Provenge / Dendreon): An autologous cell therapy approved in 2010 for prostate cancer—not melanoma. It targeted a single, non-mutated self-antigen, offered a meager four-month survival extension, was an operational nightmare to manufacture, and entirely failed to translate into a modular platform.
- T-Vec / Imlygic (Amgen): An oncolytic herpes virus approved in 2015 for direct, local lesion injection. It is an in-situ lytic agent, not a systemic personalized vaccine, and it repeatedly failed when tested in systemic combination trials with Keytruda across visceral, metastatic disease.
Moderna’s intismeran autogene (mRNA-4157 / V940) achieved what thirty years of oncology research failed to do: prove that an automated digital algorithm can sequence a patient’s unique biopsy, synthesize up to 34 distinct patient-specific neoantigens, deliver them via mRNA, and train a cytotoxic T-cell response that decisively beats the global standard of care in a randomized Phase 3 adjuvant setting.
Traditional oncology fails because when you hit a tumor with a single targeted agent, you may eliminate 95% of the cancerous cells, but the remaining 5% harboring a secondary bypass mutation survive, multiply, and kill the host.
Individualized neoantigen therapy is an algorithmic engine firing 34 distinct polyclonal targets simultaneously. It directly neutralizes cancer’s primary evolutionary weapon—clonal heterogeneity—by deploying patient-specific polyclonal immunity.
Calling this a “low-bar” victory is historical revisionism. It unlocked a biological door the entire pharmaceutical industry spent three decades trying to batter down.
2. The Micro-Cap Delusion: Stop Comparing Moderna to Lab Vendors
A peculiar strain of “circle of competence” distortion happens when micro-cap traders look at large-cap platform companies. Analysts accustomed to screening cash-strapped diagnostics names look at Moderna’s chart and think: “This looks just like a hot penny bio that got ahead of its skis.”
Moderna is not ImmunityBio. It is not GeneDx, Personalis, or Tempus AI.
Those companies operate primarily as diagnostics labs, toolmakers, or single-asset speculative plays. They rely on sample reimbursement, fight commercial insurers over CPT billing codes, and trade at the whim of retail sentiment and thematic micro-cap ETFs.
Most importantly, small biotechs suffer from a fatal structural flaw: the inevitable, momentum-killing dilution. When a sub-billion-dollar clinical biotech spikes 200%, the CFO files an S-3 shelf offering within 72 hours. They have to. They are burning cash with a ticking clock, and survival mandates dumping secondary shares on euphoric retail buyers.
Moderna does not operate under that liquidity trap:
- The Balance Sheet Fortress: Moderna entered this inflection point backed by a multi-billion-dollar cash cushion built during the pandemic windfall, reinforced by established commercial revenue from its respiratory franchise. There is zero near-term dilution overhang forcing management’s hand.
- The Merck Partnership & “Boom”: Bears love to scoff that “Moderna only gets 50% of the economics.” That is spreadsheet myopia at its finest. That 50/50 split is with Merck & Co.—the undisputed ruler of the global immuno-oncology market. Merck absorbs half of the staggering Phase 3 clinical trial costs, handles worldwide regulatory filings, and plugs the therapy directly into its global Keytruda commercial infrastructure. Moderna does not need to build a multi-billion-dollar global oncology sales force from scratch.
When the Phase 3 data was unblinded, Dr. Dean Li, President of Merck Research Laboratories, didn’t offer polite corporate PR. He captured the exact magnitude of the shift:
“It isn’t hallelujah. It’s boom.”
That was not the sigh of relief of a gambler hoping for a borderline p-value. It was the calculated assessment of Big Pharma’s sharpest R&D chief recognizing that a thirty-year scientific wall had just been pulverized.
Moderna is an institutional mega-cap asset. It does not belong in a conversation with diagnostic testing labs; it belongs in the conversation with Regeneron, Vertex, and Gilead—large-scale modular platforms capable of self-funding multi-indication expansion.
3. Steelmanning the Bear Case (And Why It Still Fails)
Intellectual honesty demands steelmanning the opposing thesis. The serious bear case was never “melanoma is easy.” The real bear case looks like this:
- The Addressable Market in Melanoma is Modest: Resected high-risk melanoma represents tens of thousands of patients annually, not hundreds of thousands. Even with premium orphan pricing, melanoma alone cannot justify an explosive valuation re-rating.
- Individualized Manufacturing is Operationally Brutal: Every batch is bespoke (N=1). Biopsy the tumor, sequence the DNA/RNA, predict the optimal epitopes, manufacture a unique mRNA cassette, sterile-filter, and infuse—all within a strict window because adjuvant patients cannot wait months. Turnaround times and high Cost of Goods Sold (COGS) are the traditional graveyard of personalized medicine.
- Payer Pushback on High-Cost Regimens: A personalized therapy priced like cell therapy in an adjuvant setting will face grueling prior-authorization warfare and resistance from single-payer healthcare systems abroad.
- Keytruda’s Looming Loss of Exclusivity (LOE): Keytruda faces patent expiration around 2028. Because the INTerpath program is anchored on Keytruda combination regimens, biosimilar entry will alter pricing, contracting, and Merck’s strategic incentives.
- The Lung Cancer Horizon is Far Away: INTerpath-002 in adjuvant non-small cell lung cancer (NSCLC) carries estimated primary-completion timelines stretching toward 2030. That is a lengthy window to underwrite platform value on faith.
Here is why that steelman still crumbles:
- On Market Size: Melanoma was never the endgame; it was the biological beachhead. The market is not pricing a single adjuvant indication; it is pricing the platform’s validated right to contest lung, bladder, renal cell, and gastrointestinal cancers. Every subsequent indication is a multi-billion-dollar call option that was violently repriced by Phase 3 proof of concept.
- On Manufacturing: This is precisely what mRNA was architected to do. Rapid, sequence-to-vial, cell-free synthesis is Moderna’s core competency—demonstrated at planetary scale during COVID. Turnaround times in clinical trials shrank to weeks, not months. Bears are describing an operational barrier that Moderna spent a decade and billions of dollars resolving.
- On Keytruda LOE: Merck is not sitting idle. Subcutaneous pembrolizumab reformulations protect the franchise, and Merck’s incentive to defend a combination that extends its anti-PD-1 leadership is paramount. An asset that enhances Keytruda’s efficacy is the most lucrative lifecycle-management tool Merck could possess. Biosimilars complicate contracting math; they do not invalidate clinical superiority.
- On Clinical Timelines: 2030 is distant, but financial markets do not wait for final study completion to adjust discount rates. Equities reprice probability of technical success (PoS) the moment biological feasibility is demonstrated. The adjuvant lung opportunity became dramatically more probable the second INTerpath-001 hit its primary endpoints.
4. Valuation Dogmatism: The Biotech Equivalent of Tesla
Attempting to model Moderna at the dawn of platform validation using a static, single-year DCF model is a fool’s errand.
Moderna is trading like the biotech equivalent of Tesla in 2019–2020.
Back then, legacy automotive analysts opened Excel, divided enterprise value by car deliveries, and shorted the stock into every parabolic run because “the multiple made no sense.” What they failed to grasp was the structural regime shift: the market ceased valuing Tesla as a cyclical capital-intensive automaker and began pricing it as an energy and software platform with near-limitless terminal value.
In biotech, when a paradigm shift occurs, historical valuation anchor points detach completely:
- Between 2020 and 2021, analysts who claimed Moderna was wildly overvalued at $60, $100, and $150 watched institutional liquidity, index rebalancing, and sheer narrative dominance carry the stock to nearly $500.
- Look at Vertex Pharmaceuticals during the clinical validation of its cystic fibrosis franchise, or Gilead Sciences during the 2013–2015 rollout of Sovaldi and Harvoni. When a therapeutic platform cures or decisively halts a fatal disease, traditional valuation multiples expand to generational extremes. Generalist institutional funds are forced to buy the equity regardless of valuation simply to prevent career-ending benchmark tracking error.
5. Striking Lightning Twice in Under a Decade
Bears cling to another cynical narrative: “Spikevax was just a temporary pandemic windfall; the sales fell off a cliff, so it doesn’t count.”
That is revisionist nonsense. In pharmaceuticals, a blockbuster is defined by the scale of its real-world impact and the commercial footprint it leaves behind. The cumulative revenue generated by Spikevax made it one of the most lucrative and rapidly scaled commercial therapeutic rollouts in medical history.
Most mid-tier biotechs spend twenty to thirty years praying a single small molecule can clear a Phase 3 study just to stave off insolvency. To pioneer a brand-new technological modality, engineer automated manufacturing from scratch, book tens of billions in commercial cash flow, and then turn around and unlock a historic breakthrough in solid-tumor oncology inside of fifteen years is virtually unprecedented.
Within 11 years of incorporation, Moderna delivered an operational year booking over $17B in top-line revenue, followed by late-stage clinical efficacy across three completely separate branches of medicine within 15 years.
Meanwhile, the commercial respiratory engine continues to quietly execute:
- In April 2026, Moderna’s mCOMBRIAX achieved European authorization as the world’s first approved flu-plus-COVID combination vaccine.
- In August 2026, the FDA approved mFLUSIVA—the first mRNA seasonal influenza vaccine cleared in the United States, showing roughly 27% superior relative efficacy over standard-of-care comparator vaccines in Phase 3 trials.
Under normal market conditions, either milestone would dominate Wall Street coverage. Today, they are treated as footnotes. Why? Because the market has caught the scent of something infinitely larger: an individualized immuno-oncology platform backed by Phase 3 data and co-piloted by Merck.
6. The Cognitive Dissonance: When Biology Meets Software
Right now, Wall Street is paralyzed by cognitive dissonance:
- Tech analysts understand zero-marginal-cost code, software compilers, and network effects, but they freeze because they don’t understand the FDA, hazard ratios, and clinical trial architecture.
- Biotech analysts understand clinical endpoints, but they are utterly incapable of modeling a platform where melanoma, lung, renal, and bladder cancer all run through the exact same automated manufacturing chassis.
Moderna’s individualized neoantigen therapy is not brewed in a massive remote bioreactor. The patient’s own cellular machinery compiles the synthetic digital code into physical antigens to train the immune system.
When a software update does not require redesigning the underlying CPU, software scales exponentially. Moderna does not need to reinvent chemistry for every new solid-tumor indication; they run the exact same sequencing pipeline, feed the data to the same algorithm, synthesize the same mRNA backbone, and let human ribosomes do the rest.
How big could this be? It has the hallmarks of an exponential paradigm shift—just like when Steve Jobs eliminated the fixed physical keyboard and replaced it with a single sheet of glass running software. Industry heavyweights and analysts relentlessly mocked it at the time. Shorting Moderna today looks like a similarly dangerous mistake.
If you are evaluating this company strictly as another Vertex, Regeneron, or Gilead, you are still thinking too small. The potential could break standard pharmaceutical assumptions the same way scaling compute broke historical hardware limits. The narrative momentum carries the same seismic weight as Moderna during the pandemic outbreak, Nvidia after ChatGPT’s debut, or Eli Lilly opening the GLP-1 floodgates.
7. Conviction Over Consensus
When I first looked at Moderna years ago, I was as skeptical as anyone. A cure synthesized inside your own cells seemed speculative—almost like science fiction. Early on, I even opted for the Pfizer vaccine simply due to the safety of legacy brand recognition.
But an interaction during the height of the pandemic stuck with me: speaking to a frontline grocery worker who was beaming with pride because she had just received her Moderna shot. It sounded emotional and anecdotal at the time, but the underlying truth never left my mind: the platform worked, it scaled under impossible conditions, and it saved lives.
I began accumulating shares of Moderna in 2023, continued buying through early 2025, and have never sold a single share.
My investment thesis was grounded in simple, first-principles logic:
- The COVID vaccine was the proof of concept. It proved mRNA could be synthesized rapidly, scaled globally, and translated by human cells safely.
- Respiratory combination vaccines evolved Moderna from a pandemic one-hit wonder into a durable commercial platform.
- Oncology is Moderna’s second act. Entering the August 19 Phase 3 readout carried immense binary risk, but the structural asymmetry on the other side of validation was generational.
The weight of this position has grown dramatically over the past several months, yet the broader story is only getting started. Skeptics will continue to stare at their spreadsheets, recalculate terminal multiples, and attempt to short into parabolic momentum.
Let them. Stepping in front of an institutionally validated, paradigm-shifting platform armed with positive Phase 3 data, zero dilution risk, the commercial engine of Merck, and violent short-covering mechanics is not financial discipline—it is pure arrogance. The skeptics think this rally is nearing its end; in reality, the paradigm shift is just beginning.


